
Key takeaways
- Full-length rails: offer more continuous side coverage but may make transfers harder and take up more space.
- Half-length or split rails: preserve an opening near the head or foot and are often more convenient for transfers.
- Assist rails or grab handles: help with repositioning or pushing up, but they are not substitutes for a properly installed transfer aid.
- Drop-down rails: can simplify caregiver access, provided the release mechanism is easy to operate and securely locks.
The best hospital beds for home care are a full-electric, low-height bed with a 36-inch mattress deck, compatible assist rails, and a capacity comfortably above the user’s weight; a semi-electric or manual bed makes more sense when budget, backup operation, or occasional use matters most.
Choosing by brand alone is risky because hospital beds differ substantially in lifting range, mattress dimensions, rail design, and assembly requirements. The right choice depends on the room, the caregiver’s ability to adjust the bed, how often it will be used, and whether transfers are the main challenge.
Our top picks

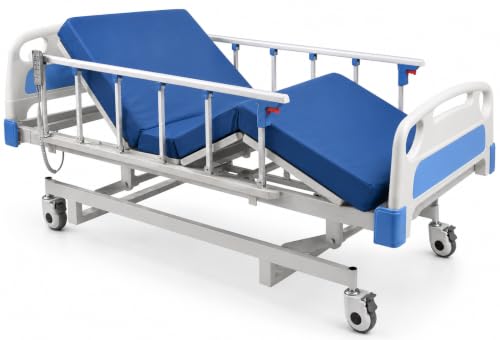
As an Amazon Associate we earn from qualifying purchases at no extra cost to you. Ratings are shown as listed on Amazon.
Best hospital beds for home care by situation
| Home-care situation | Best bed type | Useful target specifications | Why it fits |
|---|---|---|---|
| Daily bedroom use with one caregiver | Full-electric bed | 450–600 lb capacity; 15–30 in deck height; 36 x 80 in mattress | Electric controls reduce repeated manual adjustments and allow a safer working height for care. |
| Small room or fall-risk concerns | Low-height full-electric bed | Deck as low as 7–10 in; raised height of at least 24 in | Low positioning can simplify getting in and out, while a higher setting helps with changing linens. |
| Short-term recovery or backup bedroom | Semi-electric bed | 350–450 lb capacity; electric head and knee sections; manual height adjustment | It costs less and still provides powered positioning, but someone must operate a crank for height changes. |
| Limited budget or occasional use | Manual or basic semi-electric bed | 350–450 lb capacity; standard 36 x 80 in platform | Fewer motors mean fewer electrical parts, although setup and adjustments require more physical effort. |
| Larger user or frequent repositioning | Bariatric full-electric bed | 500–1,000 lb capacity; 42–54 in width; reinforced frame | The wider deck and higher rated capacity may improve fit, but the room must accommodate a larger footprint. |
What separates the leading bed categories
Full-electric beds: the easiest daily option
A full-electric bed uses a handset to raise or lower the deck and adjust the back and leg sections. This is usually the most practical choice when a person will spend many hours in bed or when a caregiver needs frequent position changes. Look for a handset with large, clearly labeled buttons and a cord long enough to reach either side of the bed.
Drive Medical’s Delta series and Invacare’s full-electric home-care beds are examples of established product families to investigate. Exact capacities and height ranges vary by model and configuration, so confirm the current specification sheet rather than assuming every bed in a series has the same rating.
Semi-electric beds: a sensible compromise
A semi-electric bed typically powers the head and knee sections but uses a manual crank for overall height. It can be a good fit when the bed will be adjusted only occasionally and a caregiver can safely operate the crank. The main ownership drawback is easy to underestimate: height changes can be difficult when the bed is occupied, and the crank may be awkward against a wall.
Manual beds: low purchase complexity, higher labor
Manual beds generally adjust through one or more cranks. They avoid motors, control boxes, and some electrical failure points, but they are less convenient for regular home care. They are best reserved for occasional use, a capable caregiver, or situations where powered equipment is not practical.
Weight capacity and mattress fit matter more than they appear
Check whether the advertised capacity means resident weight or safe working load. Safe working load can include the user, mattress, bedding, assist devices, and anything else supported by the frame. For example, a 400 lb user plus a 35 lb mattress and 15 lb of bedding already creates a 450 lb load. A bed rated at 450 lb would leave no sensible margin.
For regular use, choose a bed whose safe working load exceeds the combined load by at least 10–15% when the manufacturer permits that interpretation. A 400 lb user with 50 lb of accessories would produce a 450 lb combined load; a practical target would be a bed rated for roughly 500–520 lb or more. Ask the supplier to clarify the rating before purchase.
Most standard home-care beds accept a mattress around 36 by 80 inches, but dimensions and corner radii are not universal. A regular household twin mattress is often too thick, too soft, or incompatible with the deck’s moving sections. Use a mattress specifically labeled for the bed frame and check its maximum thickness. A mattress that is too thick can reduce the effective height of a side rail; one that is too stiff may resist articulation.
Height range, rails, and the room where the bed will go
Bedroom
A standard-height bed is usually easier to transfer into, but it should still lower enough for the user’s feet to contact the floor when sitting at the edge. A low-height model provides more adjustment range and can be useful where a fall from bed is a concern. Measure from the floor to the top of the mattress, not just to the metal deck.
Living room
Measure the bed’s full length, including the headboard and footboard, and allow space for the caregiver to walk on at least one side. A 36 by 80 inch mattress already occupies about 20 square feet; the frame, caregiver clearance, wheelchair turning space, and bedside table require considerably more. Avoid blocking heating vents, door swings, or the only route to a bathroom.
Small or shared rooms
Prioritize a narrow standard-width frame, locking casters, and rails that fold or lower without requiring removal. Split rails can provide access for transfers and may be less obstructive than full-length rails. However, rails are not universal fall-prevention devices and can create entrapment or climbing hazards. Select them with a clinician, occupational therapist, or qualified equipment provider when there is confusion, weakness, or unusual mobility.
Rail options: choose for the task, not appearance
- Full-length rails: offer more continuous side coverage but may make transfers harder and take up more space.
- Half-length or split rails: preserve an opening near the head or foot and are often more convenient for transfers.
- Assist rails or grab handles: help with repositioning or pushing up, but they are not substitutes for a properly installed transfer aid.
- Drop-down rails: can simplify caregiver access, provided the release mechanism is easy to operate and securely locks.
Do not mix a rail from one manufacturer with another bed unless compatibility is explicitly confirmed. Gaps between the mattress, rail, and frame are especially important; follow the manufacturer’s entrapment-safety instructions and inspect the fit after changing the mattress.
Setup checklist: what to confirm before the first night
- Measure the route. Record doorway widths, hallway turns, elevator dimensions, and stair constraints. A bed that fits the room may not fit through the front door assembled.
- Prepare the floor. Place the bed on a level surface, lock every caster, and avoid loose rugs that can interfere with movement or cleaning.
- Assemble by the manual. Verify that head and foot sections are fully latched, retaining pins are seated, and every rail locks in both positions.
- Connect controls carefully. Keep cables away from moving joints and casters. Use the supplied power supply and do not route cords under the frame where they can be crushed.
- Test unloaded, then loaded. Run the bed through its full height and articulation range, then check again with the mattress installed. Listen for scraping, binding, or uneven movement.
- Set a safe working height. Lower the bed for entry and exit; raise it only as needed for care. Return it to the lowest appropriate position afterward.
Ownership costs and durability realities
General market ranges are roughly $500–$1,200 for basic manual or semi-electric home-care beds, $900–$2,500 for many full-electric beds, and $2,000–$5,000 or more for bariatric or advanced low-height models. Delivery, assembly, mattress, rails, and service may cost extra. A rental can be more economical for a six-week recovery, while purchase may make more sense for long-term daily use.
The parts most likely to need attention are casters, rail-release mechanisms, handset cords, actuator cables, and mattress covers. Keep the frame dry, disinfect high-touch surfaces according to the manufacturer’s instructions, and do not saturate motors or control boxes. Inspect bolts and rail hardware periodically, especially after moving the bed.
Common mistakes include buying a mattress separately without checking dimensions, measuring only the room rather than the delivery route, selecting capacity equal to the user’s weight, and positioning the bed so a caregiver cannot reach the controls. A written measurement sheet and a confirmed compatibility list prevent most of these problems.
Bottom line
For most full-time home care, start with a full-electric, standard-width bed with a broad height range, a compatible pressure-redistributing mattress, and removable or split rails. Choose a low-height model for a compact bedroom or transfer concerns, a semi-electric model for occasional adjustments and a tighter budget, and a bariatric frame only after measuring the room and confirming the complete safe working load. Bed selection should be reviewed with a healthcare professional or occupational therapist when mobility, falls, cognition, or positioning needs are involved; this article is general information, not individualized medical advice.








